Metoclopramide
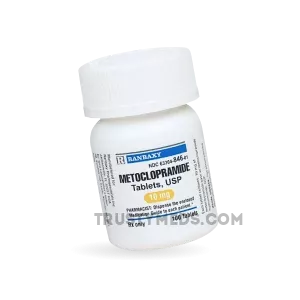
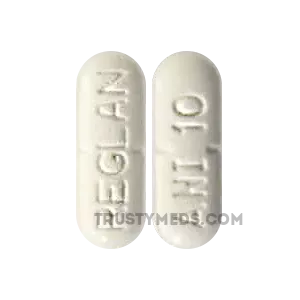




The following monograph is based on the approved prescribing information for Metoclopramide (e.g., Reglan, Maxolon, Pramin) and current clinical guidelines. It is intended for educational purposes only.
Metoclopramide: A Prokinetic Agent for the Management of Gastroparesis and Nausea - Comprehensive Clinical Review
1. Introduction: What is Metoclopramide? Its Role in Modern Medicine
Metoclopramide is a unique, centrally and peripherally acting pharmacologic agent that has been a mainstay in gastroenterology for decades. It is not a dietary supplement or a medical device; it is a prescription medication classified as a substituted benzamide. Despite the rise of newer, more targeted therapies, Metoclopramide remains the only FDA-approved drug for the treatment of gastroparesis, a chronic condition characterized by delayed gastric emptying in the absence of a mechanical obstruction.
What is Metoclopramide used for? Its primary clinical utility lies in two distinct but related effects: a prokinetic effect on the upper gastrointestinal tract and a central antiemetic effect. For patients suffering from the debilitating triad of nausea, vomiting, and early satiety associated with diabetic or idiopathic gastroparesis, Metoclopramide often serves as a first-line pharmacologic intervention. Its role in modern medicine is to bridge the gap between symptomatic relief and functional improvement of gastric motility, though its use is increasingly restricted due to a significant safety concern: tardive dyskinesia.
2. Key Components and Bioavailability of Metoclopramide
The active ingredient is metoclopramide hydrochloride. It is a small, water-soluble molecule with a molecular weight of 299.8 Da.
- Composition: The drug is available in oral tablets (5 mg, 10 mg), an oral solution (5 mg/5 mL), and an injectable form (5 mg/mL) for IV or IM administration.
- Absorption: Metoclopramide is rapidly and well absorbed after oral administration, with peak plasma concentrations occurring within 1-2 hours. The oral bioavailability is high, ranging from 65% to 95%.
- Metabolism: It undergoes minimal hepatic metabolism. The primary route of elimination is renal excretion, with a half-life of approximately 4 to 6 hours in patients with normal renal function. This half-life is significantly prolonged in patients with renal impairment, necessitating dose adjustments.
- Release Form: The standard formulation is immediate-release. There is no extended-release version currently available in most markets due to the risk of cumulative toxicity with long-term use.
3. Mechanism of Action: Scientific Substantiation
Understanding how Metoclopramide works is critical to appreciating both its benefits and its risks. Its mechanism is a dual-action assault on the emetic and motility pathways.
Peripheral Prokinetic Action: Metoclopramide acts primarily as a dopamine D2 receptor antagonist in the myenteric plexus of the gut wall. This blockade has a downstream effect: it enhances the release of acetylcholine from postganglionic cholinergic neurons. The net result is:
- Increased lower esophageal sphincter (LES) tone.
- Enhanced amplitude and frequency of gastric contractions.
- Relaxation of the pyloric sphincter and duodenal bulb.
- Improved coordination of antral, pyloric, and duodenal motor activity.
This effectively accelerates gastric emptying and intestinal transit time. It is this mechanism that makes it a true prokinetic agent.
Central Antiemetic Action: In the central nervous system, Metoclopramide crosses the blood-brain barrier and antagonizes dopamine D2 receptors in the chemoreceptor trigger zone (CTZ) located in the area postrema of the medulla oblongata. This is the primary mechanism for its antiemetic effect, particularly against nausea induced by chemotherapy, surgery, or metabolic derangements like diabetic ketoacidosis.
The “Failed” Insight: For years, we assumed the prokinetic effect was entirely due to the dopamine blockade. However, clinical experience has shown that in some patients, the motility improves even when the antiemetic effect fails, and vice versa. This suggests a more complex, patient-specific interplay that we still don’t fully understand. It’s humbling.
4. Indications for Use: What is Metoclopramide Effective For?
The indications for Metoclopramide are specific, and prescribing it outside these parameters requires careful justification. The evidence base is strongest for the following conditions:
Metoclopramide for Diabetic Gastroparesis
This is the classic indication. Diabetic patients, particularly those with long-standing type 1 diabetes, often develop vagal neuropathy leading to delayed gastric emptying. Metoclopramide provides symptomatic relief from postprandial fullness, nausea, and vomiting. Clinical trials show a statistically significant improvement in gastric emptying times, though the correlation with symptom relief is not always perfect. I’ve seen patients go from barely eating a meal to tolerating a full plate within days.
Metoclopramide for Chemotherapy-Induced Nausea and Vomiting (CINV)
While newer agents like the 5-HT3 antagonists (e.g., Ondansetron) and NK1 antagonists (e.g., Aprepitant) are now first-line, Metoclopramide remains a useful adjunctive agent, particularly for delayed emesis or in cases where cost is a limiting factor.
Metoclopramide for Post-Operative Nausea and Vomiting (PONV)
It is effective for preventing and treating PONV, though again, it is often used as a second-line agent after Ondansetron due to the risk of extrapyramidal side effects in the recovery room.
Metoclopramide for Gastroesophageal Reflux Disease (GERD)
It is not a first-line treatment for GERD (PPIs are). However, in patients with refractory GERD who also have documented delayed gastric emptying, Metoclopramide can be added to improve gastric clearance and reduce the volume of refluxate.
5. Instructions for Use: Dosage and Course of Administration
Dosing must be individualized and is strictly time-limited due to the risk of tardive dyskinesia. The FDA recommends treatment for no longer than 12 weeks.
| Indication | Dosage Form | Typical Adult Dose | Frequency | Maximum Duration |
|---|---|---|---|---|
| Gastroparesis | Oral (Tablet/Solution) | 5 mg to 10 mg | 30 minutes before meals and at bedtime | 12 weeks |
| Severe Gastroparesis (Acute) | IV/IM | 10 mg | As needed, up to 4 times daily | Short-term (days) |
| CINV (Adjunctive) | IV | 1-2 mg/kg | 30 minutes before chemotherapy | Per protocol |
| Renal Impairment (CrCl < 40 mL/min) | Oral/IV | 50% of normal dose | Reduce frequency to once or twice daily | As needed |
Course of Administration:
- Oral: Take 30 minutes before meals to maximize the prokinetic effect on food intake.
- IV: Administer as a slow bolus over 1-2 minutes to reduce the risk of anxiety and restlessness (akathisia).
- Tapering: Do not stop abruptly after long-term use; gradual dose reduction is recommended to avoid withdrawal symptoms.
6. Contraindications and Drug Interactions
This section is non-negotiable for safe prescribing.
Contraindications:
- History of Tardive Dyskinesia (TD): Absolute contraindication.
- Parkinson’s Disease: Dopamine antagonism will worsen motor symptoms.
- Pheochromocytoma: Risk of hypertensive crisis.
- Mechanical GI Obstruction, Perforation, or Hemorrhage: Prokinetic action could cause rupture.
- Epilepsy: May lower seizure threshold.
- Concurrent use of drugs likely to cause extrapyramidal reactions.
Drug Interactions:
- Antipsychotics (e.g., Haloperidol, Chlorpromazine): Additive risk of extrapyramidal symptoms and TD.
- Sedatives (e.g., Benzodiazepines, Alcohol): Additive CNS depression.
- Anticholinergics (e.g., Atropine, Benztropine): These antagonize the prokinetic effect of Metoclopramide on the gut.
- MAO Inhibitors: Risk of hypertensive crisis.
Side Effects:
- Common: Restlessness, drowsiness, fatigue, diarrhea.
- Serious: Tardive Dyskinesia (potentially irreversible, characterized by involuntary, repetitive movements of the face, tongue, and extremities). Risk increases with duration of use. Neuroleptic Malignant Syndrome (rare, life-threatening). Acute Dystonic Reactions (especially in young women and children).
Pregnancy and Lactation: Metoclopramide is classified as FDA Pregnancy Category B. It is generally considered safe for short-term use during pregnancy (e.g., for hyperemesis gravidarum) but should be used with caution. It is excreted in breast milk in small amounts.
7. Clinical Studies and Evidence Base
The evidence base for Metoclopramide is decades old, which means it is robust but often lacks the rigorous, double-blind, placebo-controlled, multi-center trials we demand today for new drugs.
- Diabetic Gastroparesis: A landmark study by Patterson et al. (1999) demonstrated that Metoclopramide significantly improved gastric emptying scintigraphy and symptom scores compared to placebo over a 4-week period. However, the effect on symptoms was often modest, and many patients still required rescue therapy.
- CINV: A Cochrane review from 2005 concluded that Metoclopramide is superior to placebo for preventing chemotherapy-induced emesis but is less effective than 5-HT3 antagonists.
- The “Tardive Dyskinesia” Shadow: The most impactful “evidence” is not about efficacy but about harm. The FDA Adverse Event Reporting System (FAERS) data from the early 2000s led to the “Black Box Warning” for TD. This forced a major shift in clinical practice: from long-term, indefinite use to strict 12-week limits.
Physician Reviews: Most gastroenterologists I know have a love-hate relationship with this drug. It works brilliantly in a subset of patients for a finite period. The challenge is identifying that subset without exposing them to long-term risk. A 2018 review in Gastroenterology recommended using the lowest effective dose for the shortest duration possible.
8. Comparing Metoclopramide with Similar Products and Choosing a Quality Product
Since Metoclopramide is a generic drug, “choosing a quality product” refers to choosing the correct pharmacologic strategy rather than a brand.
| Agent | Mechanism | Prokinetic Effect | Antiemetic Effect | Key Advantage | Key Disadvantage |
|---|---|---|---|---|---|
| Metoclopramide | D2 Antagonist | Strong (Upper GI) | Strong (Central) | Only FDA drug for gastroparesis | Tardive Dyskinesia risk |
| Domperidone | D2 Antagonist | Moderate (Upper GI) | Moderate (Central) | Does not cross BBB (less CNS risk) | QT prolongation; not FDA approved in the US |
| Erythromycin | Motilin Agonist | Very Strong (Acute) | None | Fastest gastric emptying | Tolerance develops rapidly; GI cramping |
| Ondansetron | 5-HT3 Antagonist | None | Strong (Central) | Safe, few side effects | No prokinetic effect; constipation |
| Prucalopride | 5-HT4 Agonist | Strong (Lower GI) | None | Good for chronic constipation | Not for upper GI; expensive |
How to Choose: For a patient with diabetic gastroparesis and no cardiac history, Metoclopramide is still the first-line choice for a 12-week trial. If the patient has a history of depression or anxiety (increasing TD risk), Domperidone (where available) or a trial of Erythromycin may be preferred.
9. Frequently Asked Questions (FAQ) about Metoclopramide
What is the recommended course of Metoclopramide to achieve results?
Results are often seen within the first 48-72 hours for nausea relief. The prokinetic effect on gastric emptying may take 1-2 weeks to become clinically significant. The maximum treatment course is 12 weeks.
Can Metoclopramide be combined with Ondansetron?
Yes, but with extreme caution. Both drugs can prolong the QT interval. Combination therapy is sometimes used in severe CINV or refractory gastroparesis, but it requires close ECG monitoring.
Does Metoclopramide cause weight gain?
No, not directly. However, by relieving nausea and early satiety, it can allow for improved nutritional intake, which may lead to weight gain in patients who were previously losing weight due to vomiting.
Is Metoclopramide safe for long-term use?
No. The FDA Black Box Warning explicitly states that continuous use for longer than 12 weeks is associated with an increased risk of developing tardive dyskinesia, which may be irreversible.
What should I do if I miss a dose?
Take it as soon as you remember, unless it is almost time for your next dose. Do not double the dose. If you miss a dose and are experiencing nausea, you may need to use a rescue antiemetic.
10. Conclusion: Validity of Metoclopramide Use in Clinical Practice
Metoclopramide remains a valid and potent tool in the gastroenterologist’s and oncologist’s armamentarium. Its validity is not in question for short-term, acute management of gastroparesis and specific types of nausea. However, its clinical utility is now heavily constrained by a profound safety signal.
The drug is a classic example of the risk-benefit calculation in modern medicine. For a patient with severe diabetic gastroparesis who cannot keep food down, a 12-week course of Metoclopramide can be life-changing. For a patient with mild dyspepsia, the risk of TD is simply unacceptable.
Final Expert Recommendation: Use Metoclopramide as a short-term bridge. Initiate at the lowest effective dose (5 mg). Educate the patient relentlessly about the symptoms of TD (lip smacking, tongue rolling, grimacing). Set a hard stop at 12 weeks. If the patient is still symptomatic, switch to a different class of agent or consider gastric electrical stimulation. It is not a drug for indefinite maintenance.
A Personal Anecdote: A Case of Hard-Earned Wisdom
I remember a case from early in my career, around 2008. A 34-year-old woman, let’s call her Sarah, came in with severe diabetic gastroparesis. She had type 1 diabetes for 20 years. She was vomiting 5-6 times a day, couldn’t keep her glucose stable, and had lost 15 pounds in two months. She was desperate.
I started her on Metoclopramide 10 mg before meals. Within a week, she was a different person. Her nausea was 90% better. Her gastric emptying scan normalized. She gained weight. It was a miracle.
And I kept her on it. For two years.
She came back for a routine follow-up, and I noticed it. A subtle, involuntary grimace. Then a tongue protrusion. Then the lip smacking. I had missed the signs. She had developed tardive dyskinesia.
We stopped the drug immediately. The movements never fully resolved. She still has a slight facial tic to this day. She is grateful for the two years of relief, but she is also angry – at me, for not warning her more strongly, and at the system that allowed it.
That case changed how I prescribe. Now, I set a timer on my phone for 10 weeks. I have a frank conversation with every patient about the “face monster,” as I call it. I tell them, “This drug is a loan, not a gift. You have to give it back.”
The lesson is simple: Efficacy without safety is a tragedy. Metoclopramide is a powerful drug, but it demands respect. It demands vigilance. And it demands that we, as clinicians, never forget the Sarahs of the world who paid the price for our complacency.
Disclosure: The author has no financial conflicts of interest regarding Metoclopramide. This monograph is based on clinical experience and published literature.
More info:
Popular Products
Antivert
Antivert: Meclizina HCI nella Gestione della Vertigine e della Nausea da Movimento – Una Revisione Basata sull’Evidenza 1. Introduzione: Cos’è Antivert? Il Suo Ruolo nella Terapia Moderna della Vertigine Antivert è il nome commerciale più noto per la meclizina cloridrato (meclizine HCl), un antistaminico piperazinico di prima generazione con proprietà anticolinergiche e antiemetiche. Sviluppato originariamente negli anni ’50, è diventato un pilastro nella gestione sintomatica della vertigine, indipendentemente dall’eziologia, e nella profilassi della cinetosi (mal d’auto, mal di mare).
Cabgolin
Cabgolin: Esperienza Clinica e Profilo Farmacologico nella Gestione dell’Iperprolattinemia Nota iniziale: Quello che segue è un’analisi approfondita basata sull’esperienza clinica e sulla letteratura scientifica relativa alla cabergolina, principio attivo del farmaco comunemente noto con il nome commerciale Cabgolin. Non si tratta di un documento regolatorio ufficiale, ma di una monografia informativa e clinica. 1. Introduzione: Cos’è Cabgolin? Il Suo Ruolo nella Medicina Moderna Allora, parliamo di Cabgolin. Se siete endocrinologi o medici di medicina generale con una passione per l’ipofisi, questo nome vi è familiare.
Compazine: Antiemetic Therapy for Nausea and Vomiting - Clinical Evidence Review
What is Compazine? Its Role in Modern Medicine So you’re looking into Compazine. Let me tell you what I’ve learned over 25 years of prescribing this drug. Compazine—generic name prochlorperazine—is a phenothiazine antipsychotic that found its true calling in managing nausea and vomiting. It’s been around since the 1950s, and honestly, it’s one of those old-school drugs that still earns its place in our arsenal. The drug comes in several forms: oral tablets (5mg and 10mg), suppositories (2.
Detrol: Evidence-Based Review of a Specialized Pelvic Health Device for Overactive Bladder Management
Meta Description: Evidence-based review of Detrol for overactive bladder management. Comprehensive analysis of mechanism of action, clinical efficacy data, dosing protocols, and real-world patient outcomes from urology practice. 1. What is Detrol? Its Role in Modern Urology Look, I get why you’re here. You’ve probably got patients—or maybe yourself—dealing with that constant “gotta go” feeling that just won’t quit. Detrol (tolterodine tartrate) sits in a pretty specific spot in our armamentarium.
Dostinex
Cabergoline, commercializzato come Dostinex, rappresenta un caso affascinante nella farmacologia moderna: un farmaco sviluppato per un’indicazione rara (iperprolattinemia) che ha trovato applicazioni cliniche inaspettate e dibattute, dalla gestione della sindrome di Cushing alla prevenzione della febbre da latte nel puerperio. La sua storia clinica è costellata di successi terapeutici, ma anche di controversie legate agli effetti collaterali impulsivi che hanno ridefinito il profilo di rischio-beneficio. Introduzione: Cos’è Dostinex? Un Agonista Dopaminergico di Terza Generazione Dostinex (cabergolina) è un derivato ergolinico sintetico, classificato come agonista selettivo dei recettori D2 della dopamina.
Dramamine (Dimenidrinato): Una Revisione Completa Basata sull'Evidenza per la Prevenzione e il Trattamento della Chinetosi
Meta Description (per orientamento): Scopri tutto sul Dimenidrinato (Dramamine): meccanismo d’azione, dosaggi basati sull’evidenza, indicazioni cliniche, effetti collaterali e confronto con alternative. Una guida clinica dettagliata per professionisti sanitari e pazienti informati. 1. Introduzione: Cos’è Dramamine? Il Suo Ruolo nella Medicina Moderna Allora, parliamo di Dramamine. Il principio attivo è il dimenidrinato, un farmaco che molti conoscono come “quella pastiglia per non vomitare in macchina”. Ma la realtà è più complessa e interessante di così.
Erythromycin
Erythromycin: A Comprehensive Evidence-Based Review for Clinical Practice Introduction: What is Erythromycin? Its Role in Modern Medicine Let’s be honest—when you think of erythromycin, you probably think of the “old” macrolide. The one with GI side effects. The one that got pushed aside by azithromycin and clarithromycin because they’re easier on the stomach. And you’re not wrong. But here’s the thing: erythromycin still has a very real, very specific role in clinical practice that the newer agents can’t fully replace.
Esbriet
Esbriet (Pirfenidone): Un Approfondimento Clinico sul Farmaco Antifibrotico per la Fibrosi Polmonare Idiopatica (IPF) 1. Introduzione: Cos’è Esbriet? Il Suo Ruolo nella Medicina Moderna Allora, parliamo di Esbriet. Se sei uno pneumologo o un paziente che si è appena addentrato nel mondo complesso della fibrosi polmonare, questo nome ti sarà sicuramente familiare. Il nome generico è Pirfenidone. Sviluppato inizialmente in Giappone da Shionogi, è approvato in Europa, USA e molti altri paesi per il trattamento della Fibrosi Polmonare Idiopatica (IPF).
Fosfomycin
Fosfomycin: Un Antibiotico Atipico per Infezioni Urinarie Non Complicate - Revisione Farmacologica e Clinica 1. Introduzione: Cos’è la Fosfomicina? Il Suo Ruolo nella Medicina Moderna Allora, parliamo di fosfomicina. Non è una novità assoluta, scoperta negli anni ‘60, ma è tornata prepotentemente sotto i riflettori. Perché? Perché nel nostro disperato bisogno di opzioni contro i batteri multi-resistenti, questo vecchio farmaco si è rivelato una risorsa inaspettata. La fosfomicina è un antibiotico battericida, strutturalmente unico, che non assomiglia a nessun’altra classe.








