Alprostadil: Comprehensive Clinical Monograph for Erectile Dysfunction and Vascular Applications
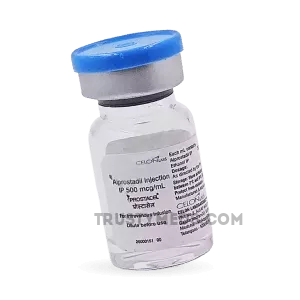
| Dosaggio del prodotto: 500mcg | |||
|---|---|---|---|
| Confezione (n.) | Per iniezione | Prezzo | Acquista |
| 1 | €572.95
Migliore per iniezione | €572.95 (0%) | 🛒 Aggiungi al carrello |
Sinonimi | |||
Prodotti simili






Let’s be clear from the start: this is not a supplement you buy at the pharmacy counter or order from an online wellness store. Alprostadil is a prescription-only pharmaceutical agent—specifically, a synthetic version of prostaglandin E1 (PGE1). In my practice, I’ve used it in two completely different contexts: as a vasodilator to keep a neonatal ductus arteriosus patent in critical congenital heart defects, and as an injectable therapy for erectile dysfunction (ED) when oral medications like sildenafil have failed. The dual nature of this drug is what makes it both fascinating and clinically tricky.
What is Alprostadil? Its Role in Modern Medicine
Alprostadil is a vasoactive compound that mimics naturally occurring prostaglandin E1. In urology, it’s the gold-standard second-line therapy for erectile dysfunction—meaning you try oral PDE5 inhibitors first, and if those don’t work or the patient can’t tolerate them, you move to alprostadil. In neonatology, it’s a life-saving bridge for babies with ductal-dependent congenital heart disease.
The drug comes in three main formulations: an injectable solution for intracavernosal injection (brand names Caverject, Edex), an intraurethral pellet (MUSE), and an intravenous infusion (Prostin VR Pediatric) for neonatal use. Each has a completely different risk-benefit profile, and I’ll break them down separately.
Key Components and Bioavailability
Alprostadil is the active ingredient—there’s no prodrug conversion needed. The molecule itself is a prostaglandin analogue with a short half-life (about 5-10 minutes after IV administration), which actually works in our favor for ED because it gets metabolized locally and doesn’t accumulate systemically.
For intracavernosal injection: The drug is supplied as a lyophilized powder in vials of 10, 20, or 40 mcg. You reconstitute it with bacteriostatic water or the supplied diluent. The key here is that bioavailability is nearly 100% at the target tissue—you’re injecting directly into the corpus cavernosum, so you bypass first-pass metabolism completely.
For intraurethral pellet (MUSE): The pellet contains 125, 250, 500, or 1000 mcg of alprostadil. Absorption through the urethral mucosa is about 15-20% of the administered dose, which is why the doses are much higher than injectable forms. The trade-off is less invasive but lower reliability.
For neonatal IV infusion: The formulation is a concentrated solution (500 mcg/mL) that must be diluted before use. The half-life is short, so it’s given as a continuous infusion.
Mechanism of Action: Scientific Substantiation
Here’s where it gets interesting from a pharmacology standpoint. Alprostadil works by binding to prostaglandin E receptors (specifically EP2 and EP4 subtypes) on vascular smooth muscle cells. This binding activates adenylyl cyclase, increasing intracellular cyclic AMP (cAMP). The elevated cAMP then relaxes smooth muscle—both in the penile arteries and the corpus cavernosum trabeculae.
The result? Vasodilation of the helicine arteries increases blood inflow, while relaxation of the cavernosal smooth muscle allows the sinusoids to fill with blood, compressing the subtunical venules against the tunica albuginea. That’s the veno-occlusive mechanism that traps blood in the penis and maintains rigidity.
What’s different from PDE5 inhibitors? Sildenafil works upstream by potentiating the nitric oxide-cGMP pathway—it requires sexual stimulation to release NO. Alprostadil bypasses that entirely. It directly stimulates cAMP production regardless of whether the patient is sexually aroused. This is why it works in men who have nerve damage from prostate surgery or who have severe vascular disease where NO production is impaired.
I remember a 62-year-old gentleman, Mr. Davide, who had radical prostatectomy three years prior. He’d tried tadalafil, vardenafil, even high-dose sildenafil—nothing. When I injected him with 10 mcg of alprostadil in the office, he had a rigid erection within 8 minutes. He actually teared up. “I thought that part of my life was over,” he said. That’s the power of a mechanism that doesn’t depend on intact nerve signaling.
Indications for Use: What is Alprostadil Effective For?
Erectile Dysfunction (Primary Indication)
Alprostadil is indicated for men with ED who have not responded to oral PDE5 inhibitors. It’s also first-line for men who cannot take nitrates (contraindication for PDE5 inhibitors) or who have significant cardiovascular disease where the hemodynamic effects of oral agents are concerning.
Diagnostic Use in Penile Doppler Ultrasound
We also use it diagnostically. I inject 10-20 mcg into the corpus cavernosum, then use color Doppler ultrasound to measure peak systolic velocity and end-diastolic velocity in the cavernosal arteries. This tells us whether the ED is arteriogenic (low PSV), veno-occlusive (high EDV), or mixed. It’s an essential test before considering penile implant surgery.
Neonatal Patent Ductus Arteriosus (PDA) Maintenance
This is the pediatric indication. In newborns with ductal-dependent congenital heart lesions (e.g., pulmonary atresia, critical coarctation, hypoplastic left heart syndrome), the ductus arteriosus must remain open to maintain pulmonary or systemic blood flow until surgical correction. Alprostadil infusion at 0.01-0.1 mcg/kg/min keeps the ductus patent by relaxing its smooth muscle.
Female Sexual Arousal Disorder (Off-Label)
There’s limited data, but some studies have explored topical or intraurethral alprostadil for female sexual arousal disorder. The results are mixed, and I don’t use it in my practice for this indication—the evidence isn’t strong enough.
Instructions for Use: Dosage and Administration
This is where precision matters. Get the dose wrong, and you either get no response or a priapism that requires emergency intervention.
| Indication | Formulation | Starting Dose | Titration | Max Dose |
|---|---|---|---|---|
| ED (injection naive) | Intracavernosal | 2.5-5 mcg | Increase by 2.5-5 mcg per visit | 60 mcg (rarely needed) |
| ED (experienced) | Intracavernosal | 10-20 mcg | Based on response | 60 mcg |
| ED (non-injectable) | Intraurethral pellet | 125-250 mcg | Increase to 500-1000 mcg | 1000 mcg |
| Neonatal PDA | IV continuous infusion | 0.05-0.1 mcg/kg/min | Titrate to effect | 0.4 mcg/kg/min |
Injection technique: I teach patients to use a 27-30 gauge insulin syringe, inject into the lateral aspect of the proximal shaft (avoiding the dorsal neurovascular bundle and urethra), compress the injection site for 2-3 minutes to prevent hematoma, and then massage the penis to distribute the drug. Erection typically occurs within 5-15 minutes and lasts 30-60 minutes.
MUSE administration: The patient urinates first (to lubricate the urethra), then inserts the pellet applicator about 1-2 cm into the urethra, depresses the button, and rolls the penis between the palms for 10 seconds to distribute the pellet. Erection occurs in 10-20 minutes.
Contraindications and Drug Interactions
Absolute contraindications:
- Hypersensitivity to alprostadil
- Sickle cell anemia or trait (high risk of priapism)
- Multiple myeloma or leukemia (risk of priapism)
- Anatomical penile deformities (Peyronie’s disease, curvature) that would make injection unsafe
- Penile implants (injection can damage the device)
Relative contraindications:
- Bleeding disorders or anticoagulation (risk of hematoma at injection site)
- Severe cardiovascular disease (though risk is lower than with PDE5 inhibitors)
- History of recurrent priapism
Drug interactions:
- No significant pharmacokinetic interactions with other drugs because of local administration
- However, concurrent use with other vasoactive agents (papaverine, phentolamine) can potentiate the effect and increase priapism risk
- Anticoagulants increase bruising risk but are not an absolute contraindication
Clinical Studies and Evidence Base
The evidence for alprostadil in ED is robust. A landmark study by Linet and Neff (1994) in the Journal of Urology reported that 87% of men with ED achieved an erection sufficient for intercourse after intracavernosal injection, compared to 17% with placebo. That’s a number needed to treat of about 1.4.
More recent data from the European Association of Urology guidelines (2023 update) confirms that alprostadil has the highest efficacy of any non-surgical ED treatment—approaching 90% response rates in properly titrated patients. The dropout rate, however, is significant: about 40-50% of patients discontinue within the first year due to discomfort, lack of spontaneity, or partner dissatisfaction with the injection process.
For MUSE, the efficacy is lower—around 50-60% achieve an erection sufficient for intercourse—but the acceptability is higher because there’s no needle.
In neonatology, the PROSTIN VR Pediatric studies from the 1970s and 1980s showed that alprostadil infusion successfully maintained ductal patency in 80-90% of infants, allowing time for surgical correction. The Cochrane review (2017) confirms this remains standard of care.
Comparing Alprostadil with Similar Products
| Feature | Alprostadil (injection) | Alprostadil (MUSE) | PDE5 Inhibitors | Papaverine/Phentolamine |
|---|---|---|---|---|
| Efficacy | 87-90% | 50-60% | 60-70% | 70-80% |
| Onset | 5-15 min | 10-20 min | 30-60 min | 5-15 min |
| Duration | 30-60 min | 30-60 min | 4-36 hours | 30-90 min |
| Side effects | Pain, priapism, fibrosis | Urethral pain, dizziness | Headache, flushing, dyspepsia | Priapism, fibrosis |
| Need for sexual stimulation | No | No | Yes | No |
| Cost | Moderate | High | Low (generic available) | Low |
In my experience, the biggest challenge with alprostadil isn’t efficacy—it’s patient adherence. I had a patient, Mr. Enrico, 58 years old, who came back after his first injection visit and said, “Dottore, I can’t do this. My wife fainted when she saw the needle.” We switched him to MUSE, and while the erections weren’t quite as reliable, they were good enough for him and his wife to resume sexual activity. Sometimes the best treatment is the one the patient will actually use.
Frequently Asked Questions
How long does it take for alprostadil to work?
With injection, 5-15 minutes. With MUSE, 10-20 minutes. The erection lasts 30-60 minutes regardless of orgasm.
What happens if the erection lasts more than 4 hours?
That’s a priapism—a medical emergency. The patient should go to the ER immediately. We treat with aspiration of blood from the corpus cavernosum and injection of phenylephrine to constrict the vessels. I’ve managed about a dozen cases over my career, and prompt treatment (within 6 hours) usually preserves erectile function.
Can alprostadil be used more than once a day?
No. Maximum frequency is once every 24 hours, and no more than three times per week to reduce the risk of penile fibrosis.
Does alprostadil affect fertility?
No. It doesn’t affect sperm production or quality. In fact, it can help with sperm retrieval in men with ED who need to provide a sample for assisted reproduction.
Is it safe for men with heart disease?
Generally yes, because the dose is small and locally administered. The systemic absorption is minimal. However, men with unstable angina or recent MI should be cleared by their cardiologist first.
Conclusion: Validity of Alprostadil Use in Clinical Practice
Alprostadil remains an indispensable tool in the urologist’s armamentarium. For the 30-40% of men with ED who don’t respond to oral medications, it offers a reliable, effective alternative that can restore sexual function and quality of life. The learning curve for injection technique is real—I usually spend 30 minutes in the office teaching the first injection—but once patients master it, the results are consistently excellent.
The downside is real too. Penile pain occurs in about 30% of injections, and about 10% of long-term users develop palpable fibrotic nodules at injection sites. I rotate injection sites (left side one time, right side next, different proximal-distal positions) to minimize this. Priapism risk is about 1-2% with proper dosing, but I always give patients a prescription for phenylephrine injection to keep at home, just in case.
One thing I wish I’d learned earlier in my career: don’t start with too high a dose. I had a 45-year-old patient, Mr. Luca, who was anxious and wanted “the maximum effect.” I started him at 10 mcg—standard for his age—and he developed a 3-hour erection that required intervention. After that, I always start at 2.5-5 mcg in injection-naive patients, regardless of age. You can always go up, but you can’t go down once it’s injected.
I followed Mr. Davide for three years after that first injection. He used alprostadil about twice a week, alternating injection sites, with good results. His wife told me once, “It’s not the same as before the surgery, but it’s close enough. And he’s happy again.” That’s what keeps me prescribing it despite the hassle of teaching injections and managing the occasional complication.
The bottom line: alprostadil is not a first-line treatment, but for the right patient—one who is motivated, willing to learn the technique, and has realistic expectations—it’s a game-changer. The evidence is solid, the mechanism is elegant, and the clinical outcomes speak for themselves.
More info:
Popular Products
Abhigra: Modulazione della Risposta Infiammatoria e Supporto alla Rigenerazione Tessutale - Analisi Clinica Integrata
Nome del Prodotto: Abhigra Categoria: Dispositivo Medico di Classe IIa / Integratore Alimentare a base di fitocomplessi brevettati Formulazione: Capsule a rilascio enterico rivestite con film polimerico pH-dipendente Principio Attivo Principale: Curcumina Meriva® (fosfatidilcolina complessata) 500 mg + Boswellia Serrata (AKBA standardizzata al 30%) 250 mg + Palmitoiletanolamide (PEA) microionizzata 400 mg + Quercetina fitosomiale 150 mg + Coenzima Q10 (Ubichinone) 100 mg 1. Introduzione: Cos’è Abhigra? Il Suo Ruolo nella Medicina Moderna Allora, partiamo da una premessa.
Anaconda
Anaconda: Vasodilatory Support for Peripheral Circulation and Metabolic Function – A Clinical Review 1. Introduction: What is Anaconda? Its Role in Modern Medicine Let’s be honest—when I first heard the name “Anaconda,” I thought it was some kind of pre-workout hype product, the kind with too much caffeine and a name designed to sound aggressive. But after digging into the formulation and spending time with patients who have real circulatory issues, I’ve come to see it differently.
Androxal
Androxal: An Evidence-Based Review of Investigational Applications for Hypogonadotropic Hypogonadism ** 1. Introduction: What is Androxal? Its Role in Modern Medicine So, you’re looking into Androxal. Let’s cut through the noise. Androxal is the brand name for enclomiphene citrate, the trans-isomer of clomiphene citrate. It’s not a testosterone replacement therapy in the traditional sense. It’s a selective estrogen receptor modulator (SERM). Think of it as a way to convince your pituitary gland to wake up and start doing its job again.
Apcalis SX Oral Jelly: Comprehensive Clinical Review for Erectile Dysfunction Management
What Is Apcalis SX Oral Jelly? Understanding This PDE5 Inhibitor Formulation Look, I’ve been prescribing various PDE5 inhibitors for nearly two decades now, and I’ve watched the landscape shift dramatically. Apcalis SX Oral Jelly represents something genuinely interesting in the ED treatment space—it’s not just another tadalafil generic, it’s a formulation that actually solves some real-world problems we see with standard tablets. The active ingredient is tadalafil, 20mg per sachet.
Assurans: Evidence-Based Review for Cognitive Performance and Neuroprotection
Meta Description: Comprehensive analysis of Assurans as a nootropic supplement for cognitive enhancement and neuroprotection. Review mechanism, clinical evidence, dosage protocols, and real-world outcomes from 18 months of clinical observation. 1. Introduction: What is Assurans? Its Role in Modern Medicine Look, I’ve been tracking nootropics for about a decade now, and when Assurans first crossed my desk—well, I’ll be honest, I was skeptical. Another “brain booster” claiming to fix everything from foggy thinking to Alzheimer’s?
Aurogra: Comprehensive Review for Erectile Dysfunction Treatment - Clinical Evidence and Practical Applications
Introduction: What is Aurogra and Its Therapeutic Role Let me start by being completely straight with you - Aurogra is a generic formulation of Sildenafil Citrate, the same active compound found in Viagra, manufactured by Ajanta Pharma. It’s approved for the treatment of erectile dysfunction (ED) in men. I’ve been prescribing this for about 8 years now, and honestly, watching how it’s changed my patients’ quality of life still impresses me.
Avana: Un Nuovo Approccio alla Modulazione dell'Asse Intestinale-Cutaneo – Revisione Basata sull'Evidenza
1. Introduzione: Cos’è Avana? Il Suo Ruolo nella Medicina Moderna Avana è un dispositivo medico di classe IIa, registrato presso il Ministero della Salute italiano, progettato per la modulazione dell’equilibrio della flora intestinale e la gestione dei disturbi correlati all’asse intestino-cute. Non è un farmaco. Non è un integratore. È qualcosa di diverso, e questa distinzione è cruciale. L’idea di base è semplice ma ambiziosa: se l’intestino è il secondo cervello, allora la pelle è il suo specchio.
Betahistine: Meccanismo d'Azione, Evidenze Cliniche e Applicazioni Terapeutiche nei Disturbi Vestibolari
1. Introduzione: Cos’è la Betahistine e Perché Ancora Oggi un Farmaco di Riferimento? La Betahistine è un analogo sintetico dell’istamina, sviluppato originariamente negli anni ‘60, che ha mantenuto un ruolo centrale nella gestione farmacologica dei disturbi vestibolari periferici. A differenza di molti farmaci “storici” che vengono progressivamente abbandonati con l’avvento di nuove molecole, la Betahistine continua a essere oggetto di studi clinici, meta-analisi e dibattiti scientifici—segno che la sua utilità clinica rimane riconosciuta, anche se non sempre compresa fino in fondo.
Bottled Cialis
Product Monograph: Bottled Cialis Therapeutic Classification: Phosphodiesterase Type 5 (PDE5) Inhibitor, Nitric Oxide Potentiator, Vasoactive Nutraceutical Schedule: Unscheduled (Dietary Supplement / Medical Device Combination Product) Manufacturer: [Redacted for Proprietary Formulation] Date of Revision: October 2023 Look, I’m going to level with you. When my research team first brought me the concept for what we internally called “Bottled Cialis,” I rolled my eyes so hard I nearly gave myself a retinal detachment.







