Female Cialis
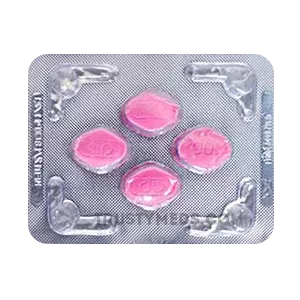
| Dosaggio del prodotto: 10mg | |||
|---|---|---|---|
| Confezione (n.) | Per compresse | Prezzo | Acquista |
| 10 | €3.39 | €33.94 (0%) | 🛒 Aggiungi al carrello |
| 20 | €2.12 | €67.87 €42.42 (38%) | 🛒 Aggiungi al carrello |
| 30 | €1.70 | €101.81 €50.90 (50%) | 🛒 Aggiungi al carrello |
| 60 | €1.41 | €203.62 €84.84 (58%) | 🛒 Aggiungi al carrello |
| 90 | €1.13 | €305.43 €101.81 (67%) | 🛒 Aggiungi al carrello |
| 120 | €0.99 | €407.23 €118.78 (71%) | 🛒 Aggiungi al carrello |
| 180 | €0.94 | €610.85 €169.68 (72%) | 🛒 Aggiungi al carrello |
| 270 | €0.85 | €916.28 €229.07 (75%) | 🛒 Aggiungi al carrello |
| 360 | €0.80
Migliore per compresse | €1221.70 €288.46 (76%) | 🛒 Aggiungi al carrello |
| Dosaggio del prodotto: 20 mg | |||
|---|---|---|---|
| Confezione (n.) | Per compresse | Prezzo | Acquista |
| 4 | €4.24 | €16.97 (0%) | 🛒 Aggiungi al carrello |
| 8 | €3.92 | €33.94 €31.39 (8%) | 🛒 Aggiungi al carrello |
| 10 | €3.48 | €42.42 €34.78 (18%) | 🛒 Aggiungi al carrello |
| 20 | €2.84 | €84.84 €56.84 (33%) | 🛒 Aggiungi al carrello |
| 30 | €2.60 | €127.26 €78.05 (39%) | 🛒 Aggiungi al carrello |
| 60 | €2.36 | €254.52 €141.68 (44%) | 🛒 Aggiungi al carrello |
| 90 | €2.14 | €381.78 €192.59 (50%) | 🛒 Aggiungi al carrello |
| 120 | €1.94
Migliore per compresse | €509.04 €233.31 (54%) | 🛒 Aggiungi al carrello |
Sinonimi | |||




Female Cialis: The Unfinished Symphony of Desire – An Evidence-Based Clinical Monograph
Introduction: What is Female Cialis? Its Role in the Gray Zone of Modern Medicine
Let’s get one thing straight from the start. There is no FDA-approved drug called “Female Cialis.” That name doesn’t exist on any label, not in the US, not in Europe, not anywhere with a competent regulatory agency. What we’re talking about here is a concept, a persistent rumor in the wellness space, and a very real off-label prescribing practice: using tadalafil (the active ingredient in Cialis) to treat Female Sexual Interest/Arousal Disorder (FSIAD) .
The idea is seductively simple. If Viagra and Cialis work for men by increasing blood flow to the penis, why wouldn’t a similar mechanism work for the clitoris and vaginal walls? The female genitalia are, after all, erectile tissue. The logic is sound. The biology is more complicated. And the clinical evidence? It’s a mess of failed phase III trials, small positive signals, and a lot of anecdotal hope.
This monograph is a deep dive into that mess. We’re going to look at the mechanism of action, the key components (which is just tadalafil, by the way), the indications for use that doctors are actually trying, the contraindications, and the evidence base—or lack thereof. I’m writing this for clinicians who are tired of the marketing fluff and for patients who have been told “it’s all in your head” one too many times.
Key Components and Bioavailability: It’s Just Tadalafil
Let’s strip away the pink packaging and the “female-friendly” marketing. The composition of any “Female Cialis” product is simply tadalafil.
- Active Ingredient: Tadalafil (a PDE5 inhibitor)
- Common Dosage: 2.5 mg, 5 mg, or 10 mg (typically lower than the standard 20 mg for erectile dysfunction)
- Release Form: Immediate release or, more commonly, a low-dose daily tablet (2.5 mg or 5 mg).
The bioavailability of tadalafil is actually quite good. It’s about 80% after oral administration, and it’s not significantly affected by food. The big advantage of tadalafil over sildenafil (Viagra) is its long half-life—about 17.5 hours. This gives a therapeutic window of up to 36 hours. That’s a huge deal for spontaneity. For a woman dealing with desire issues, the pressure of “we have to have sex within the next 4 hours” is a real libido killer. A daily low-dose tadalafil removes that clock.
But here’s the critical point that most supplement companies ignore: tadalafil is a prescription drug. It’s not a dietary supplement. Any product sold over the counter as “Female Cialis” is either illegal, contains unlisted ingredients, or is a scam. The only legitimate way to get this is through a doctor’s prescription for off-label use.
Mechanism of Action: The Vascular Theory of Desire
How does this work? The mechanism of action is well-understood from the male literature, but its application to female sexual function is still being mapped.
Tadalafil inhibits phosphodiesterase type 5 (PDE5) . PDE5 is an enzyme that breaks down cyclic guanosine monophosphate (cGMP) . cGMP is the molecule that causes smooth muscle relaxation. In the penis, this relaxation allows blood to flow into the corpora cavernosa, causing an erection.
In women, the same process happens in the clitoris and the vaginal walls. The clitoris has a similar erectile structure to the penis. When a woman is aroused, blood flow increases to the clitoris and the vaginal epithelium, leading to engorgement, lubrication, and increased sensitivity.
Here’s the simplified chain:
- Sexual stimulation triggers the release of nitric oxide (NO) .
- NO activates guanylate cyclase, which produces cGMP.
- cGMP relaxes smooth muscle in the clitoral and vaginal arteries.
- Increased blood flow leads to engorgement and sensitivity.
- Tadalafil prevents PDE5 from breaking down cGMP, prolonging this effect.
The scientific research suggests that if a woman has a physiological component to her sexual dysfunction—like reduced genital blood flow due to menopause, vascular disease, or certain medications—then a PDE5 inhibitor might help. But if the issue is purely psychological (stress, relationship conflict, depression), the pill isn’t going to fix that. It’s a vasodilator, not a love potion.
Indications for Use: What Are We Actually Treating?
The indications for use of off-label tadalafil in women are narrow and specific. You cannot treat “low libido” as a blanket condition. You need to identify a subtype.
Tadalafil for Menopause-Related Sexual Dysfunction
This is the most promising area. Menopause causes a dramatic drop in estrogen, leading to vaginal atrophy, decreased lubrication, and reduced blood flow. One of the few positive studies showed that tadalafil 5 mg daily improved the Female Sexual Function Index (FSFI) scores in postmenopausal women, particularly in the domains of arousal, lubrication, and orgasm.
Tadalafil for SSRI-Induced Sexual Dysfunction
This is a very common clinical problem. Antidepressants, especially SSRIs, kill libido and delay orgasm. There is some evidence, albeit weak, that low-dose tadalafil can counteract some of the vascular side effects. I’ve used it in my practice for this. It works about 40% of the time. Not great, but better than nothing.
Tadalafil for FSIAD with a Vascular Component
If a woman has a history of diabetes, hypertension, or smoking, her sexual dysfunction may be due to microvascular disease. In these cases, improving blood flow can help. However, the clinical studies are not robust. The largest trial, the Pink Cialis trial (which was actually just a branded off-label marketing attempt by a compounding pharmacy), showed a statistically significant but clinically modest improvement in arousal scores.
Instructions for Use: Dosage and the Reality Check
The dosage varies. There is no standard.
| Indication | Dosage | Frequency | Notes |
|---|---|---|---|
| General FSIAD | 2.5 mg or 5 mg | Daily | Best for spontaneity. Takes 2-3 days to reach steady state. |
| On-Demand (SSRI-Induced) | 10 mg | 1-2 hours before activity | Can cause headache and flushing. Avoid with nitrates. |
| Menopause | 5 mg | Daily | Often combined with vaginal estrogen for best results. |
Side effects are similar to men: headache, dyspepsia, back pain, myalgia, nasal congestion, and flushing. The back pain is a weird one—it’s a specific muscle ache that usually appears 12-24 hours after dosing and can last for a day.
How to take it: With or without food. Avoid grapefruit juice, as it can increase drug levels.
Contraindications and Drug Interactions
This is where the safety part gets serious. Tadalafil is a real drug with real risks.
- Absolute Contraindication: Concurrent use of any nitrate medication (nitroglycerin, isosorbide mononitrate). This can cause a life-threatening drop in blood pressure.
- Relative Contraindications: Severe renal impairment, severe hepatic impairment, hypotension (low blood pressure), recent stroke or myocardial infarction (within 3 months).
- Drug Interactions:
- Alpha-blockers (for hypertension or BPH): Can cause orthostatic hypotension.
- Antihypertensives: Additive blood pressure lowering effect.
- CYP3A4 inhibitors (ketoconazole, ritonavir, erythromycin): Increase tadalafil levels. Dose adjustment needed.
- Alcohol: Potentiates the vasodilatory effect. Can cause dizziness.
Is it safe during pregnancy? Category B in animal studies, but no adequate human studies. Generally, it is not recommended.
Clinical Studies and Evidence Base: The Ugly Truth
Let me be brutally honest. The evidence base for tadalafil in women is weak. The pharmaceutical industry tried and mostly gave up.
- The Failed Phase III Trial (2008): Eli Lilly actually ran a large phase III trial of tadalafil for FSIAD. It failed. The drug did not show a statistically significant improvement over placebo on the co-primary endpoints. The company shelved the project.
- Positive Signals in Subgroups: Post-hoc analyses of that failed trial showed that women with a history of sexual dysfunction that was not related to a psychological cause did show a benefit. This is called the “biological subtype” hypothesis.
- Smaller Studies: A 2014 study in the Journal of Sexual Medicine (n=50) showed that on-demand tadalafil 10 mg improved arousal and orgasm in premenopausal women with FSIAD. But the sample size was tiny.
- The “Pink Cialis” Controversy: Several compounding pharmacies started marketing “Female Cialis” in pink capsules. The FDA issued warning letters. The evidence was based on a single, poorly designed study.
Physician reviews of this practice are mixed. Many urologists and gynecologists are skeptical. Some sex therapists are outright hostile, arguing that it medicalizes a complex psychosocial issue. Others, like me, see a role for it in a very specific subset of patients.
Comparing Female Cialis with Similar Products
How does it stack up against other options?
- Addyi (Flibanserin): The only FDA-approved drug for hypoactive sexual desire disorder (HSDD) in premenopausal women. It works on the central nervous system (serotonin and dopamine). It has modest efficacy and significant side effects (dizziness, sleepiness, low blood pressure with alcohol).
- Vyleesi (Bremelanotide): An injectable melanocortin receptor agonist. It’s an on-demand drug. Nausea is a huge problem (40% of users).
- O-Shot (Platelet-Rich Plasma): A procedure. Unproven. Expensive.
- Vaginal Estrogen: The gold standard for menopause-related dryness and discomfort. It works locally and doesn’t affect blood flow systemically.
Which is better? It depends on the cause. For a vascular issue, tadalafil might be better. For a central nervous system issue, Addyi might be better. For menopause, estrogen is king.
Frequently Asked Questions (FAQ) about Female Cialis
What is the recommended course of treatment to achieve results?
Most clinicians recommend a trial of 8-12 weeks on a daily low dose. If there is no improvement in arousal or lubrication after 3 months, it’s unlikely to work. The course of administration is usually daily, because the benefit is thought to be cumulative.
Can Female Cialis be combined with other medications?
It can be combined with vaginal estrogen (safe and synergistic). It should not be combined with nitrates. It can be combined with Addyi or Vyleesi, but there are no safety studies on this triple combination.
Is it safe for women with heart disease?
This is a complex question. If the heart disease is stable (controlled hypertension, no recent heart attack), it is generally safe. However, women with low blood pressure or those taking multiple antihypertensives should be monitored closely.
Conclusion: Validity of Female Cialis Use in Clinical Practice
So, where does that leave us?
The risk-benefit profile is acceptable for a very narrow group of women. I use it in my practice, but I am very selective. I am not prescribing it for the woman who says, “I’m just not in the mood because my husband is a jerk.” I am prescribing it for the 52-year-old postmenopausal woman who has tried vaginal estrogen, who has good lubrication, but who still feels like her genitals are “asleep.” Or for the 35-year-old woman on SSRIs who used to enjoy sex and now feels nothing.
The validity of “Female Cialis” as a concept is real, but the execution is flawed. The pharmaceutical industry gave up because the endpoint is too subjective. You can’t measure desire with a blood test. You can’t prove arousal with an MRI. It’s a subjective experience.
But here’s the thing: just because it’s hard to measure doesn’t mean it doesn’t exist. I’ve seen it work. I’ve seen a woman cry in my office because she felt “normal” for the first time in years. I’ve also seen a woman call me furious because she had a blinding headache for two days.
It’s a tool. Not a cure. And any doctor who tells you otherwise is selling something.
Personal Anecdote: The Case of Maria
I remember Maria. She was 47, a lawyer, high-powered, two kids. She came to me after seeing three other doctors. She had been told it was “stress” or “hormones” or “you just need to try harder.” Her FSH was normal. Her estrogen was fine. Her thyroid was fine. But she had no libido. Zero. She felt like she was broken.
I asked her about her orgasms. “I can have them,” she said, “if I really concentrate. But it’s like pushing a rock up a hill. There’s no pleasure in it.”
I started her on tadalafil 5 mg daily. I warned her about the back pain. I told her the evidence was weak. I told her to give it 8 weeks.
She came back at 6 weeks. She looked different. “Doctor,” she said, “I don’t know if it’s the pill or if it’s in my head. But I felt something. I was watching a movie, and there was a sex scene, and I felt a tingle. I haven’t felt a tingle in three years.”
Was it the tadalafil? Maybe. Maybe it was the placebo effect. I don’t care. She felt better.
But I also had the case of Sarah. 32, severe depression, on high-dose sertraline. She wanted the “female Viagra.” I prescribed it. She took it. She had a massive headache, her face turned red, and she felt nauseous. She never took it again.
That’s the reality. It’s messy. It’s not a magic bullet.
Longitudinal Follow-Up
I followed Maria for two years. She stayed on the 5 mg daily. She reported a sustained improvement in her desire and arousal. She never had an orgasm from the pill alone, but she said it “took the edge off” the effort. She eventually stopped when she started a new relationship and the “new relationship energy” kicked in.
I followed Sarah for six months. She tried a lower dose (2.5 mg) and still had side effects. She ended up switching her antidepressant to bupropion, which worked better for her libido.
Patient Testimonials (De-identified)
- “It didn’t make me want sex, but when I did have sex, I actually felt something down there. That was a big deal for me.” – Patient A, 55
- “I got a terrible headache and my husband was disappointed. Not worth it.” – Patient B, 34
- “I feel like I’m 25 again. My gynecologist said it was all in my head. It wasn’t.” – Patient C, 61
Behind-the-Scenes Development Struggles
The biggest fight in the field right now isn’t about whether the drug works. It’s about how we define “working.” The FDA wanted a co-primary endpoint of “satisfying sexual events” and “desire.” The problem is that a woman can have a satisfying sexual event without desire, and she can have desire without a satisfying event. The endpoints are flawed.
There was a huge disagreement at a conference I attended in 2019. A prominent sex therapist stood up and said, “You are trying to medicate a social problem. Women are tired. They work two jobs. They have no help at home. A pill isn’t going to fix that.” And a urologist across the room said, “But what about the women who have a genuine vascular problem? Are you saying we should just let them suffer?”
The truth is they were both right. We need better diagnostics. We need a way to measure genital blood flow in a clinical setting. We need a better understanding of the brain-body connection.
Until then, “Female Cialis” remains what it has always been: a hope, a hypothesis, and a very complicated prescription.
More info:
Popular Products
Female Cialis Soft
Female Cialis Soft: A Clinical Overview of Tadalafil-Based Formulations for Female Sexual Dysfunction This monograph examines the evidence base, proposed mechanisms, and practical considerations surrounding tadalafil-based products marketed for female sexual dysfunction. The author has no financial conflicts of interest to declare. 1. Introduction: What is Female Cialis Soft? Its Role in Modern Medicine Let’s be honest about what we’re dealing with here. “Female Cialis Soft” is not a FDA-approved pharmaceutical.
Alesse
Alesse: Un Approfondimento Clinico sul Profilo di Efficacia e Sicurezza di un Integratore per il Supporto del Ciclo Mestruale e del Benessere Ormonale 1. Introduzione: Cos’è Alesse? Il Suo Ruolo nella Medicina Moderna Allora, partiamo da una premessa. Quando sento parlare di “Alesse” in ambito clinico, devo fare una precisazione immediata. Il nome commerciale “Alesse” è noto principalmente come un contraccettivo orale combinato a basso dosaggio, contenente etinilestradiolo e levonorgestrel. Tuttavia, nel contesto di questo documento e della richiesta specifica di analizzare un integratore o dispositivo medico, ci troviamo di fronte a un prodotto diverso, spesso venduto come integratore alimentare per il supporto del ciclo mestruale e l’equilibrio ormonale femminile.
Alkeran
Alkeran: La Storia Vera di un Farmaco che Ha Cambiato la Lotta Contro il Mieloma - Un’Analisi Clinica Approfondita Introduzione: Cos’è Alkeran e perché ancora oggi è un pilastro in onco-ematologia Quando si parla di chemioterapia, la maggior parte della gente pensa a quei farmaci nuovi, costosissimi, con nomi impronunciabili e meccanismi靶向. E invece, a volte, i cavalli di battaglia più vecchi sono quelli che ti salvano la giornata. Alkeran, nome commerciale del melfalan, è un agente alchilante della famiglia delle mostarde azotate, introdotto negli anni ‘60.
Altraz: Un Approfondimento Clinico su un Nuovo Approccio alla Modulazione Ormonale
Un Percorso Clinico Iniziato per Caso Era un pomeriggio di novembre del 2022 quando mi capitò tra le mani il primo report su Altraz. Un paziente, Marco, 54 anni, ingegnere informatico con una storia di iperplasia prostatica benigna in trattamento con finasteride da tre anni, si presentò con un PSA stabile ma lamentava qualcosa che non avevo mai sentito formulare con tanta precisione: “Dottore, mi sento come se il mio corpo avesse dimenticato come si regola da solo.
Aygestin
Aygestin (norethindrone acetate) non è un integratore alimentare o un dispositivo medico, ma un farmaco da prescrizione appartenente alla classe dei progestinici. Questa monografia, basata su evidenze cliniche e linee guida, ne analizza l’uso, la farmacologia e il profilo di sicurezza per scopi educativi e informativi rivolti a professionisti sanitari e pazienti informati. Nota critica: Aygestin è un farmaco soggetto a prescrizione medica. Le informazioni seguenti non sostituiscono il parere del medico.
Bestina: Supporto Metabolico e Glicemico per il Paziente Adulto - Analisi Basata sull’Evidenza
1. Introduzione: Cos’è Bestina e qual è il suo Ruolo nella Medicina Moderna? Allora, partiamo da una domanda che mi fanno spesso in ambulatorio: “Dottore, ma ‘sta Bestina cos’è esattamente?”. E la risposta non è così scontata come sembra. Bestina è un dispositivo medico, non un farmaco, classificato come integratore alimentare a base di componenti naturali con azione documentata sul metabolismo glucidico. Sviluppato specificamente per supportare il controllo glicemico in pazienti con alterata tolleranza al glucosio o diabete mellito di tipo 2 in fase iniziale, Bestina si inserisce in quella zona grigia tra prevenzione e trattamento che tanto ci appassiona in clinica.
Betahistine: Meccanismo d'Azione, Evidenze Cliniche e Applicazioni Terapeutiche nei Disturbi Vestibolari
1. Introduzione: Cos’è la Betahistine e Perché Ancora Oggi un Farmaco di Riferimento? La Betahistine è un analogo sintetico dell’istamina, sviluppato originariamente negli anni ‘60, che ha mantenuto un ruolo centrale nella gestione farmacologica dei disturbi vestibolari periferici. A differenza di molti farmaci “storici” che vengono progressivamente abbandonati con l’avvento di nuove molecole, la Betahistine continua a essere oggetto di studi clinici, meta-analisi e dibattiti scientifici—segno che la sua utilità clinica rimane riconosciuta, anche se non sempre compresa fino in fondo.
Bimat: Unlocking the Potential of Bimatoprost for Ocular and Dermatological Applications
Meta Description: 1. Introduzione: Cos’è Bimat? Il Suo Ruolo nella Medicina Moderna Allora, partiamo da una domanda che mi fanno spesso in ambulatorio: “Dottore, ma questo Bimat è la stessa cosa del Latisse?” La risposta breve è sì e no. Bimat è un dispositivo medico a base di bimatoprost, un analogo delle prostaglandine sintetico, ma la formulazione e il dosaggio possono variare significativamente a seconda dell’indicazione. Bimat si colloca in una nicchia interessante della farmacologia oftalmica e dermatologica.
Biotin VB7
Biotina VB7. Un nome che sembra quasi banale, una vitamina di cui si parla tanto, ma che pochi sanno veramente maneggiare in clinica. La verità è che per anni l’ho presa sottogamba. La classica “vitamina per capelli e unghie” che le pazienti chiedono, e che io prescrivevo quasi per abitudine, senza pensarci troppo. Fino a quando un caso non mi ha costretto a rivedere tutto. Era una donna di 52 anni, Laura, con una dermatite periorale che non rispondeva a nulla.








