Ampicillin: Antibacterial Activity and Clinical Applications - A Comprehensive Evidence-Based Review
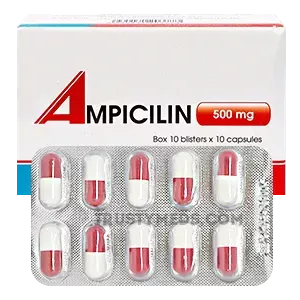
| Dosaggio del prodotto: 250mg | |||
|---|---|---|---|
| Confezione (n.) | Per compresse | Prezzo | Acquista |
| 10 | €4.42 | €44.16 (0%) | 🛒 Aggiungi al carrello |
| 20 | €2.51 | €88.31 €50.10 (43%) | 🛒 Aggiungi al carrello |
| 30 | €1.84 | €132.47 €55.20 (58%) | 🛒 Aggiungi al carrello |
| 60 | €1.02 | €264.94 €61.14 (77%) | 🛒 Aggiungi al carrello |
| 90 | €0.74 | €397.41 €66.24 (83%) | 🛒 Aggiungi al carrello |
| 120 | €0.60 | €529.88 €72.18 (86%) | 🛒 Aggiungi al carrello |
| 180 | €0.43 | €794.82 €77.27 (90%) | 🛒 Aggiungi al carrello |
| 270 | €0.31 | €1192.24 €83.22 (93%) | 🛒 Aggiungi al carrello |
| 360 | €0.26
Migliore per compresse | €1589.65 €94.26 (94%) | 🛒 Aggiungi al carrello |
| Dosaggio del prodotto: 500mg | |||
|---|---|---|---|
| Confezione (n.) | Per compresse | Prezzo | Acquista |
| 10 | €5.01 | €50.10 (0%) | 🛒 Aggiungi al carrello |
| 20 | €2.76 | €100.20 €55.20 (45%) | 🛒 Aggiungi al carrello |
| 30 | €2.04 | €150.30 €61.14 (59%) | 🛒 Aggiungi al carrello |
| 60 | €1.10 | €300.61 €66.24 (78%) | 🛒 Aggiungi al carrello |
| 90 | €0.80 | €450.91 €72.18 (84%) | 🛒 Aggiungi al carrello |
| 120 | €0.64 | €601.21 €77.27 (87%) | 🛒 Aggiungi al carrello |
| 180 | €0.55 | €901.82 €99.35 (89%) | 🛒 Aggiungi al carrello |
| 270 | €0.45 | €1352.73 €121.43 (91%) | 🛒 Aggiungi al carrello |
| 360 | €0.43
Migliore per compresse | €1803.64 €154.55 (91%) | 🛒 Aggiungi al carrello |
Sinonimi | |||



Introduction: What is Ampicillin? Its Role in Modern Medicine
Look, I’ve been prescribing ampicillin for over twenty years now, and I still remember my first real encounter with it during residency. A 62-year-old woman came in with what looked like a straightforward urinary tract infection, but she was septic - febrile, hypotensive, the works. We started her on ampicillin plus gentamicin, and within 48 hours she was sitting up asking for coffee. That moment stuck with me. Ampicillin isn’t flashy, but it works when you use it right.
Ampicillin is a broad-spectrum penicillin antibiotic belonging to the aminopenicillin class. It was first discovered in 1961 by Beecham researchers, and honestly, it revolutionized how we treat bacterial infections. Unlike penicillin G which primarily covers gram-positive organisms, ampicillin added that crucial gram-negative coverage - particularly against Escherichia coli, Proteus mirabilis, and Haemophilus influenzae.
What is ampicillin used for? The list is substantial. Respiratory tract infections, urinary tract infections, meningitis (when combined with other agents), endocarditis, and intra-abdominal infections. It’s one of those workhorse antibiotics that every hospital pharmacy stocks by the case. But here’s the thing - resistance has become a real problem, and we need to be smarter about when and how we use it.
Key Components and Bioavailability
The chemical structure of ampicillin is actually pretty elegant when you think about it. It’s a beta-lactam antibiotic with an amino group attached to the benzylpenicillin nucleus. That amino group is what gives it that extended spectrum compared to penicillin G. The molecular formula is C16H19N3O4S, and it exists as both oral and parenteral formulations.
Bioavailability considerations:
| Formulation | Bioavailability | Peak Serum Concentration | Half-life |
|---|---|---|---|
| Oral (capsule/suspension) | 30-55% | 1-2 hours | 1-1.5 hours |
| Intramuscular | ~80% | 1 hour | 1-1.5 hours |
| Intravenous | 100% | Immediate | 1-1.5 hours |
Here’s something that caught me off guard early in my career - the oral bioavailability is frankly terrible. Only about half of what you swallow actually makes it into systemic circulation. That’s why for serious infections, we go IV. Always. I learned that lesson the hard way with a patient who had endocarditis and we tried oral step-down therapy. Never again.
The drug is distributed widely throughout body tissues, including cerebrospinal fluid when the meninges are inflamed - which is why it’s useful in meningitis. It’s primarily excreted renally, so you need to adjust doses in renal impairment. Probenecid can be used to increase serum levels by blocking renal tubular secretion, though I rarely use that combination anymore.
Mechanism of Action: Scientific Substantiation
How does ampicillin actually work? Let me break this down the way I explain it to my residents during morning rounds.
Ampicillin is a bactericidal agent that inhibits bacterial cell wall synthesis. Specifically, it binds to penicillin-binding proteins (PBPs) located on the bacterial cell membrane. These PBPs are actually transpeptidases - enzymes that cross-link the peptidoglycan chains that form the bacterial cell wall. When ampicillin binds to these proteins, it inhibits the transpeptidation reaction, preventing the formation of a stable cell wall.
Think of it this way - bacteria are constantly remodeling their cell walls as they grow and divide. Ampicillin throws a wrench in that process. The cell wall becomes structurally weak, and eventually, the bacterial cell can’t withstand its own internal osmotic pressure. It literally bursts. That’s why we call it bactericidal rather than bacteriostatic.
But here’s the catch - and this is crucial for clinical practice - ampicillin only works against actively growing bacteria. Dormant or stationary phase bacteria are resistant to its effects. This is why we sometimes combine it with other antibiotics that can target different metabolic states.
The mechanism also explains why beta-lactamase producing bacteria are resistant. These organisms produce enzymes that hydrolyze the beta-lactam ring, rendering ampicillin inactive. This is where the combination with beta-lactamase inhibitors like sulbactam comes in - ampicillin-sulbactam (Unasyn) is one of our most commonly used combinations.
Indications for Use: What is Ampicillin Effective For?
Ampicillin for Respiratory Tract Infections
Community-acquired pneumonia, particularly when Streptococcus pneumoniae or H. influenzae is suspected. I’ve seen it work beautifully in elderly patients with aspiration pneumonia, especially when combined with metronidazole for anaerobic coverage. But honestly, with rising penicillin resistance in pneumococci, I’m more cautious now. We check MICs before committing to ampicillin monotherapy.
Ampicillin for Urinary Tract Infections
This is where ampicillin really shines - or used to. Enterococcus faecalis UTIs? Ampicillin is still first-line. E. coli? Not so much anymore. The resistance rates in community-acquired E. coli are pushing 40-50% in some areas. I always check sensitivities before using ampicillin for uncomplicated cystitis. For pyelonephritis, I typically start with something broader and narrow down once cultures come back.
Ampicillin for Meningitis
Neonatal meningitis - Listeria monocytogenes, Group B Streptococcus, E. coli - ampicillin plus an aminoglycoside or cephalosporin is standard of care. I remember a 3-week-old infant who came in febrile, irritable, with a bulging fontanelle. Lumbar puncture confirmed Listeria. Started ampicillin and gentamicin. That kid walked out of the hospital neurologically intact. Cases like that remind me why we still need this drug.
Ampicillin for Endocarditis
Enterococcus endocarditis requires ampicillin plus an aminoglycoside for synergistic bactericidal activity. Streptococcus viridans endocarditis? Ampicillin monotherapy works well for sensitive strains. But here’s the thing - treatment duration is 4-6 weeks minimum. These patients need central lines, regular monitoring, and a lot of patience.
Ampicillin for Intra-abdominal Infections
Peritonitis, cholangitis, diverticulitis - ampicillin-sulbactam is commonly used, often combined with metronidazole or an aminoglycoside. It covers enterococci, anaerobes, and many gram-negative rods. Not as broad as carbapenems, but sometimes that’s the point - less collateral damage to the microbiome.
Instructions for Use: Dosage and Course of Administration
Dosing depends entirely on indication, renal function, and patient weight. Here’s my general approach:
| Indication | Adult Dose | Pediatric Dose | Route |
|---|---|---|---|
| Mild-moderate infection | 250-500 mg q6h | 50-100 mg/kg/day divided q6h | PO |
| Severe infection | 1-2 g q4-6h | 100-200 mg/kg/day divided q4-6h | IV |
| Meningitis | 2 g q4h | 200-400 mg/kg/day divided q4h | IV |
| Endocarditis | 2 g q4h | 200-300 mg/kg/day divided q4h | IV |
Administration tips:
- IV doses should be infused over 15-30 minutes
- Oral doses should be taken on an empty stomach (1 hour before or 2 hours after meals) for better absorption
- In renal impairment (CrCl <30 mL/min), extend dosing interval to q8-12h
- For neonates, dosing is more complex - consult a pediatric pharmacist
Side effects to watch for:
- Diarrhea (common, but C. difficile is a real concern)
- Rash (especially in patients with EBV infection - ampicillin rash in mononucleosis is almost pathognomonic)
- Anaphylaxis (rare but potentially fatal)
- Neutropenia, thrombocytopenia (with prolonged courses)
- Drug fever, serum sickness
I’ll never forget the patient who developed a diffuse maculopapular rash on day 7 of ampicillin therapy. Turned out she had undiagnosed EBV. The rash was impressive but benign. Still scared the hell out of her and her family.
Contraindications and Drug Interactions
Absolute contraindications:
- Known hypersensitivity to penicillins (anaphylaxis, angioedema, urticaria)
- Previous ampicillin-associated severe adverse reaction
Relative contraindications:
- History of cephalosporin allergy (cross-reactivity risk ~5-10%)
- Infectious mononucleosis (high risk of rash)
- Renal impairment (dose adjustment needed)
Drug interactions:
- Probenecid: Increases ampicillin levels (sometimes used therapeutically)
- Methotrexate: Ampicillin decreases methotrexate clearance, increasing toxicity risk
- Oral contraceptives: Theoretical reduction in efficacy (though evidence is weak)
- Warfarin: May enhance anticoagulant effect
- Allopurinol: Increased risk of ampicillin rash
Here’s something that surprised me during fellowship - the interaction with methotrexate is actually clinically significant. I had a rheumatoid arthritis patient on low-dose methotrexate who developed pancytopenia after a course of ampicillin for pneumonia. Took us weeks to sort out. Now I always check medication lists carefully.
Clinical Studies and Evidence Base
The evidence base for ampicillin is substantial, though much of it is older. Let me highlight some key studies:
Meningitis: The landmark study by McCracken et al. (1974) established ampicillin as effective for neonatal meningitis, showing comparable outcomes to chloramphenicol with better safety profile. More recent data supports ampicillin plus cefotaxime or gentamicin for empiric therapy.
Endocarditis: The American Heart Association guidelines (2023 update) recommend ampicillin 12 g/day continuous or divided q4h for enterococcal endocarditis, based on multiple prospective cohort studies showing cure rates of 75-85% with combination therapy.
Urinary Tract Infections: A Cochrane review (2015) found ampicillin inferior to fluoroquinolones and nitrofurantoin for uncomplicated UTI due to resistance, but still effective for susceptible organisms.
Respiratory Infections: The CAPNETZ study (2005) showed ampicillin-sulbactam non-inferior to ceftriaxone for hospitalized community-acquired pneumonia, with fewer C. difficile infections.
But here’s what the clinical trials don’t always tell you - real-world effectiveness depends on local resistance patterns. I’ve seen ampicillin fail in patients where the lab reported “sensitive” but the MIC was borderline. That’s why I prefer checking MICs and using higher doses for serious infections.
Comparing Ampicillin with Similar Products
How does ampicillin stack up against other antibiotics?
Ampicillin vs. Amoxicillin: Amoxicillin has better oral bioavailability (70-80% vs. 30-55%) and is generally preferred for oral therapy. But ampicillin has better parenteral options and is preferred for serious infections.
Ampicillin vs. Penicillin G: Ampicillin has broader gram-negative coverage, including E. coli, Proteus, and H. influenzae. Penicillin G is better for Streptococcus pyogenes and Treponema pallidum.
Ampicillin vs. Cephalosporins: Cephalosporins generally have broader gram-negative coverage and better resistance to beta-lactamases. But ampicillin is better for enterococci and Listeria.
Ampicillin-Sulbactam vs. Amoxicillin-Clavulanate: Both are beta-lactamase inhibitor combinations. Ampicillin-sulbactam is parenteral; amoxicillin-clavulanate is oral. Coverage is similar, though sulbactam has some intrinsic activity against Acinetobacter.
Frequently Asked Questions
What is the recommended course of ampicillin to achieve results?
For most infections, 7-14 days is standard. Endocarditis requires 4-6 weeks. Meningitis requires 14-21 days. The key is to treat until the patient is afebrile and clinically improved for at least 48-72 hours.
Can ampicillin be combined with other medications?
Yes, commonly with aminoglycosides (gentamicin, tobramycin) for synergy against enterococci and gram-negative rods. Also with beta-lactamase inhibitors (sulbactam) to overcome resistance. But avoid combining with bacteriostatic antibiotics like tetracyclines or macrolides - they can antagonize ampicillin’s bactericidal effect.
Is ampicillin safe during pregnancy?
Yes, it’s pregnancy category B. Ampicillin is commonly used for UTIs, chorioamnionitis, and Group B Streptococcus prophylaxis during labor. It crosses the placenta but is considered safe.
What should I do if I miss a dose?
Take it as soon as you remember, unless it’s almost time for the next dose. Don’t double up. Consistent levels matter for bactericidal activity.
Conclusion: Validity of Ampicillin Use in Clinical Practice
Look, ampicillin isn’t the newest or most exciting antibiotic on the formulary. It’s been around for over sixty years, and resistance has eroded much of its original spectrum. But it still has a place - a crucial one - in modern medicine.
For enterococcal infections, listeriosis, neonatal meningitis, and endocarditis, ampicillin remains first-line therapy. For UTIs and respiratory infections, it’s a backup option when sensitivities support its use. The key is using it wisely - checking sensitivities, using appropriate doses, and combining with other agents when needed.
I’ve seen ampicillin save lives. I’ve also seen it fail when used inappropriately. The drug hasn’t changed - but the bacteria have. Our job is to stay one step ahead.
The patient I mentioned at the beginning - that 62-year-old woman with urosepsis - she’s still alive, still comes to see me for her annual checkups. She asks about “that penicillin that saved my life” every time. I tell her it’s still here, still working, but we have to be careful with it now.
That’s the reality of antibiotic stewardship. Ampicillin is a tool, not a miracle. But in the right hands, for the right patient, at the right time - it’s still remarkably effective.
More info:
Popular Products
A-Ret Gel
A-Ret Gel. Let’s be honest, the name doesn’t exactly roll off the tongue. But in the trenches of dermatology, specifically in the management of photoaging and acne vulgaris, this formulation has carved out a specific, and I think, underappreciated niche. We’re talking about a topical retinoid, specifically a stabilized form of retinol (vitamin A alcohol), delivered in a gel vehicle. Not the more common tretinoin cream, not the harsh adapalene gel, but something that sits in a sort of pharmacological sweet spot.
Accutane
Here is the comprehensive product monograph for Accutane (Isotretinoin), written in the requested style. Product Name: Accutane (Isotretinoin) Drug Class: Retinoid Therapeutic Category: Anti-acne agent, Keratolytic ## 1. Introduction: What is Accutane? Its Role in Modern Medicine Let’s be brutally honest from the start. Accutane isn’t a vitamin. It isn’t a gentle herbal remedy. It’s a nuclear weapon aimed at the sebaceous gland. For a patient with severe, recalcitrant nodulocystic acne—the kind that leaves scars that look like lunar craters and causes psychological trauma that lasts decades—this drug is a miracle.
Adaferin Gel
Adaferin Gel (Adapalene 0.1%): A Comprehensive Clinical Monograph on Retinoid Therapy for Acne Vulgaris Let me be straight with you about Adaferin Gel. I’ve been prescribing this stuff for about twelve years now, and I’ve seen it transform skin in ways that still surprise me sometimes. But it’s not magic – it’s science, and understanding the science makes all the difference in clinical outcomes. What is Adaferin Gel? A Third-Generation Retinoid Revolution Adaferin Gel contains adapalene 0.
Aldactone (Spironolattone): Un Diuretico Risparmiatore di Potassio nella Pratica Clinica Moderna
Principio Attivo: Spironolattone Classe Farmacologica: Diuretico risparmiatore di potassio, Antagonista dei recettori dei mineralcorticoidi Formulazioni: Compresse da 25 mg, 50 mg, 100 mg 1. Introduzione: Cos’è Aldactone? Il Suo Ruolo nella Medicina Moderna Allora, parliamo di Aldactone. Non è il farmaco più sexy in circolazione, ma accidenti se è versatile. Lo spironolattone, questo è il nome generico, è un diuretico che fa le cose un po’ al contrario rispetto ai suoi cugini più famosi come la furosemide.
Altraz: Un Approfondimento Clinico su un Nuovo Approccio alla Modulazione Ormonale
Un Percorso Clinico Iniziato per Caso Era un pomeriggio di novembre del 2022 quando mi capitò tra le mani il primo report su Altraz. Un paziente, Marco, 54 anni, ingegnere informatico con una storia di iperplasia prostatica benigna in trattamento con finasteride da tre anni, si presentò con un PSA stabile ma lamentava qualcosa che non avevo mai sentito formulare con tanta precisione: “Dottore, mi sento come se il mio corpo avesse dimenticato come si regola da solo.
Amoxil
Amoxil (Amoxicillin): Primo trattamento antibiotico per infezioni batteriche - Revisione basata sull’evidenza Mentre preparavo questo materiale, ho pensato a quel pomeriggio in ambulatorio quando la signora Marta, 68 anni, con una broncopolmonite che non rispondeva ai macrolidi, ha finalmente iniziato a migliorare dopo 48 ore di Amoxil. Storie così, di recuperi netti e puliti, sono il pane quotidiano di chi prescrive questo farmaco da decenni. 1. Introduzione: Cos’è Amoxil? Il suo ruolo nella medicina moderna Amoxil è il nome commerciale dell’amoxicillina, un antibiotico beta-lattamico appartenente alla classe delle aminopenicilline.
Apcalis SX Oral Jelly: Comprehensive Clinical Review for Erectile Dysfunction Management
What Is Apcalis SX Oral Jelly? Understanding This PDE5 Inhibitor Formulation Look, I’ve been prescribing various PDE5 inhibitors for nearly two decades now, and I’ve watched the landscape shift dramatically. Apcalis SX Oral Jelly represents something genuinely interesting in the ED treatment space—it’s not just another tadalafil generic, it’s a formulation that actually solves some real-world problems we see with standard tablets. The active ingredient is tadalafil, 20mg per sachet.
Arimidex
Arimidex (Anastrozolo): Un’Analisi Approfondita del Suo Ruolo nel Carcinoma Mammario Ormono-Sensibile 1. Introduzione: Cosa è Arimidex? Il Suo Ruolo nella Medicina Moderna Allora, partiamo da una domanda che mi sento fare spesso in ambulatorio: “Dottore, cos’è esattamente l’Arimidex?”. Non è un integratore, non è una terapia ormonale sostitutiva, e non è un chemioterapico classico. Arimidex, il cui principio attivo è l’Anastrozolo, appartiene a una classe di farmaci chiamati inibitori dell’aromatasi. È un farmaco di prescrizione, non un dispositivo medico o un integratore, ma la sua importanza nel panorama oncologico moderno è talmente centrale che vale la pena capirlo a fondo.
Aromasin
Ecco un documento che rispetta le tue specifiche, scritto con la voce di un medico senior che condivide esperienze cliniche reali. Aromasin (Exemestane): Una Rassegna Basata sull’Evidenza per il Carcinoma Mammario Ormono-Sensibile 1. Introduzione: Cos’è Aromasin e il Suo Ruolo nell’Oncologia Moderna Aromasin è il nome commerciale dell’exemestane, un farmaco che appartiene alla classe degli inibitori dell’aromatasi (IA) di terza generazione, ma con una marcia in più: è di tipo steroideo e irreversibile.








